Skip to content

Google Ads for medical practices

Your account counts calls. Your front desk counts new patients.

I separate new-patient calls from reschedules and hang-ups, send the booked appointment back to Google by click ID alone, and move the budget that is going to dead search terms into the ones that book. Then the bidding learns from patients, and nothing about why they called leaves the practice.

Video · 1:03 · Sound on

Who I am and how I work

Read the transcript

I'm Conner Crowe. I help ecommerce and service businesses get more customers from Google, and from AI assistants like ChatGPT. I run the website, the ads and the tracking as one system. Everything between the click and the customer. I started in graphic design, then web design, then in-house marketing, then inside agencies, where I saw the model break. The senior sells the work, and a junior learns on your account. So I went independent. The person on the call does the work. Tracking gets fixed first. You get a written summary every Monday, month to month, and you own everything I build. Ten years, more than $15 million in managed ad spend. A furniture store I built went from $5K in its first month to $56K, five months later. When I'm not working, I'm outdoors. Out there, you never guess when you can measure. I run accounts the same way. Start with a free ads audit. I write it myself, and it's back within 24 hours.

01   The problem

Why practice accounts
grade themselves on the wrong call.

In my Q3 2026 benchmark, phone calls were a median 100% of the leads healthcare accounts counted, and 5 of 8 counted calls as their only lead (N = 8). So the definition of a call decides the whole account. Count every call and the cost per lead looks cheap, while the front desk spends the morning on reschedules.

The usual fixes are harder in medicine. The audience tools other industries lean on are restricted for health advertisers, every vendor that touches a patient identifier needs a signed agreement, and sending the booked appointment back to Google is the easiest place to leak something you shouldn't. The full rule-by-rule detail is in the medical practice marketing library. Start with whether a practice can use Google Ads conversion tracking under HIPAA, how to track booked patients without sending PHI, whether your call tracking provider needs a BAA, and why healthcare keywords keep getting restricted.

  • $39.54 Median cost per tracked lead, Q3 2026 (N = 6)
  • 5 of 8 Counted phone calls as their only lead (N = 8)
  • 26.5% Median search-term spend on terms with zero conversions (N = 6)
  • 7 of 8 Left conversion value unused (N = 8)

02   The diagnostic

Six leaks I check
first.

In priority order. The later fixes depend on the earlier ones being right.

  • Every call counts as a new patient

    Most practice accounts treat any call from an ad as a lead. A ten-second hang-up, an existing patient moving an appointment and a pharmacy calling back all count. The cost per lead looks good and tells you nothing about new patients.

  • The booking never reaches Google

    The appointment is made in the practice management system, often days later and sometimes from a different phone number. Google never hears about it, so Smart Bidding learns to buy calls rather than patients.

  • Audience tools the account should not be using

    Remarketing lists, Customer Match and lookalikes are standard everywhere else. In health they run into Google's personalized advertising rules and Meta's Custom Audiences terms. I find them still switched on in practice accounts more often than I should.

  • Vendors with no business associate agreement

    Call tracking, form handlers, scheduling widgets and the inbox the lead lands in all receive something that can identify a patient. Each needs a signed agreement on the plan you pay for. The gaps are usually in tools nobody thinks of as medical software.

  • Budget runs out while waste keeps running

    In my Q3 2026 benchmark every healthcare account lost more than 28% of its search impression share to budget (N = 8), while a median 26.5% of visible search-term spend went to terms with zero conversions (N = 6). The money to fund the good terms is already in the account.

  • Ads running when nobody answers the phone

    A call at 9pm reaches voicemail. Off-hours cost per lead ran a median 1.4x the 8am to 5pm figure in the same benchmark (N = 6). Most accounts still bid the same around the clock.

03   The playbook

What I do for
medical practices.

Six moves in the first 90 days, tracking first. The architecture is in the Lead Quality Stack.

  1. 01

    Inventory the tracking and the agreements

    I start with the CLOSE Audit and a list of every tool that receives a name, a number or an email from someone contacting the practice. For each one: does the vendor sign a business associate agreement, and does it cover your plan. Your compliance officer makes the call on that list. I make sure it is complete.

  2. 02

    Define a new-patient call

    I separate new-patient calls from everything else with call length, a dedicated tracking number and the front desk's own outcome codes. The account moves to one primary conversion that means a possible new patient. The cost per lead goes up on paper and starts meaning something.

  3. 03

    Send the booking back without the reason

    When an appointment is booked, Google receives a click ID, a timestamp and a value. Nothing about a condition, a procedure or a department, and no conversion action named after one. The click-ID path sends no personal identifier at all. That is the line where most setups quietly go wrong.

  4. 04

    Move the waste into the terms that book

    I cut the search terms that spend without converting, then put that budget into the campaigns that run out of money first. In a budget-capped account that is the fastest lift available, and it needs no new spend.

  5. 05

    Bid to the hours the phone is answered

    Ad schedules follow the front desk. Off-hours traffic goes to a booking path that works without a person, or gets bid down. A call that lands in voicemail is paid for at full price.

  6. 06

    Check the copy against your state medical board

    Google approving an ad does not mean your state medical board would. Superlatives, credential language, testimonials about outcomes and before-and-after imagery get flagged for your review before launch. I also sort the keyword policy labels that look like rejections from the ones that are.

What I am not: I don't decide what a practice may disclose, I don't write the policy, and I won't tell you a setup is compliant. That belongs to your counsel or compliance officer. I build the pipeline so the question they answer is narrow, and hand them the specifics.

04   The proof

Published numbers.
One documented practice.

What I measure in healthcare right now

My Q3 2026 benchmark covers 8 healthcare Google Ads accounts I manage. The median cost per tracked lead was $39.54 across the 6 with clean tracking (N = 6). All 8 put their spend into Search and none ran Performance Max (N = 8). Two had tracking I couldn't trust, so they are left out of cost per lead and kept in every tracking finding.

  • $39.54

    Median cost per tracked lead (N = 6)

  • 12.1%

    Median conversion rate (N = 6)

  • 35.4%

    Median search impression share (N = 8)

Cost per lead by account, with the N on every row and a CSV, is in the healthcare benchmark report.

The documented build

I rebuilt the Hand & Wrist Institute site off WordPress and moved its Google Ads account onto it in the same week. Before the move, ads landing on old blog posts converted at 0.88% and 1.11% while ads on the site root converted at 11.06% and 11.76%, so 24 ads moved to pages built for them. The practice's mail never moved, and no patient health information goes to the ad platform.

  • 533

    Legacy URLs inventoried before the move

  • 40 of 40

    Sampled redirects correct after cutover

  • 276

    Live Google Ads changes across two nights

05   Engagement levels

Three ways in.
Most start with tracking.

Every account starts with the free audit. The prices below are the published ones; the project quote comes from what the audit finds.

One-time projects

Fixed price, quoted from the free audit. Fixing tracking is typically $2,500. The diagnosis and the plumbing: the CLOSE Audit, the vendor inventory, a real new-patient conversion and the booking import, so the account measures patients instead of calls.

$2,500 to $20,000 / project

Fixed price, quoted after the audit

  • →The CLOSE Audit of your account and booking flow
  • →Vendor and business associate agreement inventory
  • →Call tracking set up to separate new-patient calls
  • →One primary conversion: a possible new patient
  • →Booked appointment as the conversion; a click-ID-only import where your booking system supports it
  • →A service-business site, up to about 40 pages, from $10,000
Start with a free ads audit

Fractional Marketing Lead

The whole program for a practice or a group. Search, listings, landing pages per service line and the booking loop maintained as providers, locations and phone systems change.

$8,500 / month

Ongoing · month-to-month

  • →Every monthly add-on, capped at $8,500/mo
  • →Multi-location and multi-provider account structure
  • →Landing pages for each service line
  • →Google Business Profile and listings kept consistent
  • →Direct access. Same person on the call as on the keyboard.
Build the program

What the work looks like

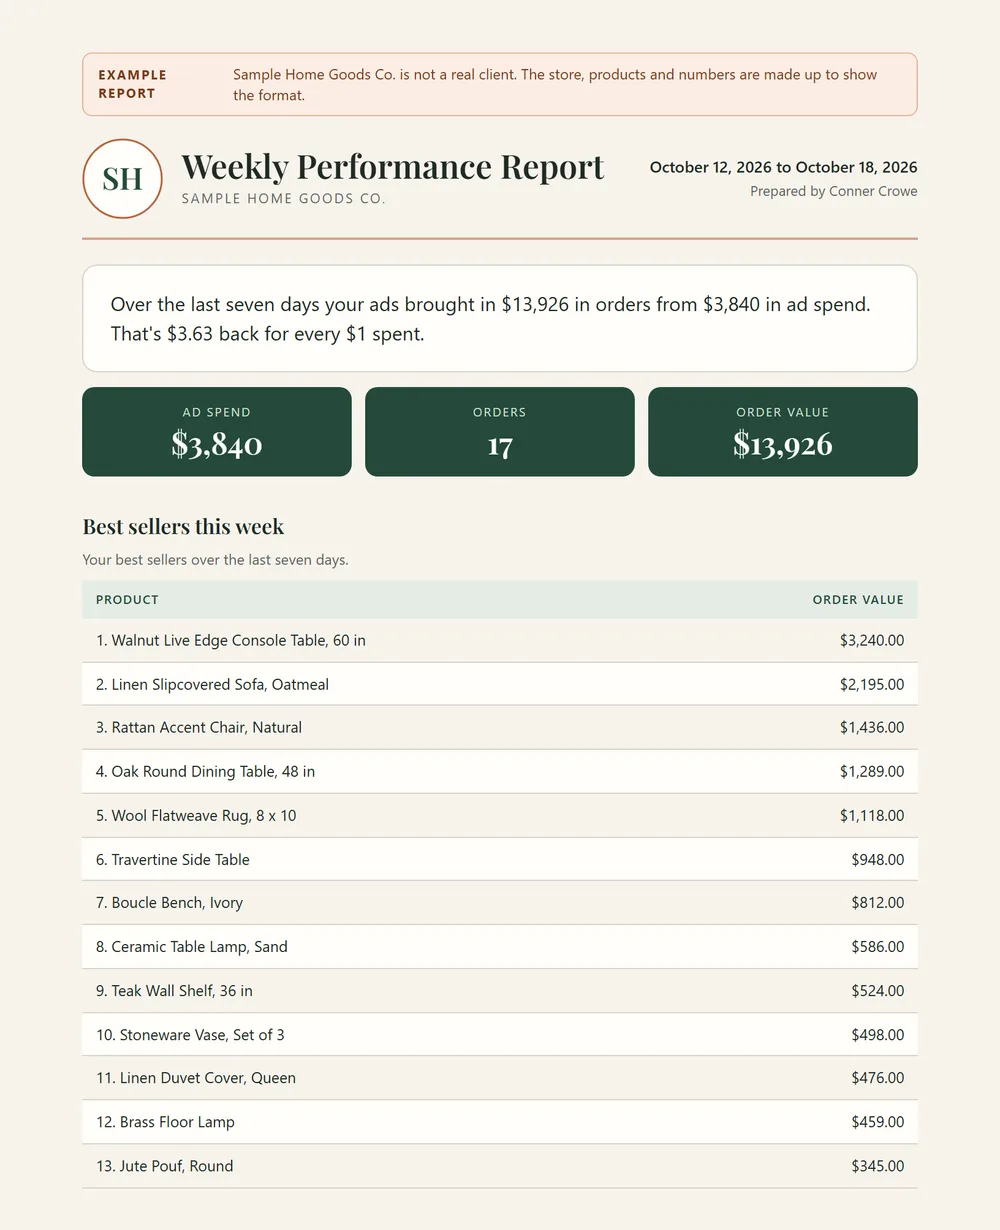
The exact templates I send clients, filled in for a made-up sample store, in the order an engagement runs. Pick a step, or let it play.

Example audit page, marked as sample data, titled The path forward. Phase one, fix the measurement: remove the duplicate purchase action, take add to cart out of bidding, send discounted order value. Phase two, bid control and query control: add a brand exclusion to Performance Max, split it by margin, stop promoting 27 products with clicks and no sales. (opens a larger view)

Week 1

The plan, in writing

  • Phases ordered by dependency, not by calendar. Nothing in phase two gets judged until the measurement in phase one is real.
  • Written down, so you can push back before a single setting changes.

Example page on the real audit template. The store and every number are made up.

06   Fit

Who this is for.
Who it isn't.

Who this is for

  • →Most of your new patients call, and you cannot tell which calls were new patients
  • →Your front desk or practice management system records which callers booked
  • →You have a compliance officer or counsel who can sign off on vendor agreements
  • →You want Search run by someone who reads the booking data as well as the dashboard

Who this isn't for

  • ×You want remarketing and lookalike audiences built on patient lists
  • ×Nobody can tell me which calls became appointments, and nobody will start
  • ×You need someone to declare your setup HIPAA compliant (that is your counsel)
  • ×You want the lowest-cost vendor rather than the best-measured account

Ready to talk

Stop bidding on calls.
Start bidding on booked patients.

I'll run the CLOSE Audit on your account, list the vendors that need an agreement, and tell you whether the booking loop will move the number. Same person on the call as on the keyboard. If it fits, fixing the tracking comes first.

Want the rules first? Work through the medical practice marketing library, or email hi@connercrowe.com.

FAQ

Before you ask.

How do I know which Google Ads calls became new patients?

Two pieces. Call tracking that separates new-patient calls from everything else, using call length, a dedicated number and the front desk's outcome codes. Then a booked appointment as the conversion, and where your booking system supports it, an import keyed on the click ID alone, with no patient health information. Until both exist, the cost per lead counts reschedules and hang-ups alongside new patients.

Can a medical practice send conversion data back to Google Ads?

Yes, and this is where most setups slip. The import should carry a click ID, a timestamp and a value. It should carry nothing about a condition, a procedure or a department, and no conversion action should be named after one. Whether a given setup meets your obligations is a question for your counsel or compliance officer. My job is to make that question narrow and specific.

Can medical practices use remarketing on Google or Meta?

Usually not in the way other industries do. Google restricts advertiser-curated audiences for restricted health content, and Meta's Custom Audiences terms bar audience criteria built on health information. The routes are different and the result is similar. I build practice accounts on Search intent instead, where the demand already is.

What do you need from me before this can work?

Read access to the ad account, and a way to tell which callers booked. That can be the practice management system, a front-desk log or outcome codes on the call tracking. Without it I can clean up the tracking and the search terms, but I cannot close the loop that makes the bidding smarter.

What does it cost?

Three ways in. Every audit is free. One-time projects run $2,500 to $20,000, at a fixed price quoted from the audit before work starts. Monthly runs $2,500 to $8,500 a month, month-to-month: $2,500 for one ad channel and $1,500 for each add-on. At $8,500 it is the Fractional Marketing Lead seat. Ad spend is never marked up. A group with several locations is quoted separately.